
Overview
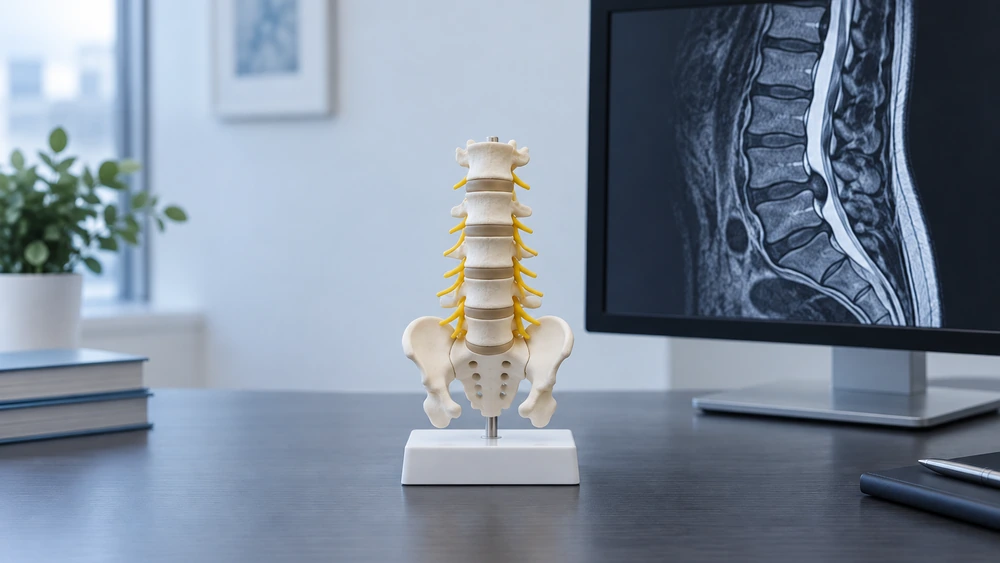
Lumbar decompression surgery aims to create more space around the spinal nerves in the lower back. This condition often arises due to compression from thickened ligaments, enlarged joints, bony overgrowth, or a bulging disc. The procedure involves removing a small amount of bone and soft tissue from the back of the spine to relieve pressure.
Several techniques may be employed during lumbar decompression surgery, depending on the specific findings of the patient’s condition. These techniques include:
- Laminectomy or Laminotomy: These procedures widen the spinal canal.
- Foraminotomy: This technique widens the openings where nerve roots exit.
- Discectomy: This involves removing disc material pressing on a nerve root.
- Flavectomy: This procedure removes thickened ligament to alleviate nerve compression.
In cases where there is significant instability or deformity, lumbar decompression may be combined with spinal fusion. This combination alters both the operation and the recovery timeline and is discussed thoroughly with the patient in advance.
Generally, lumbar decompression surgery is considered when other non-surgical methods have been exhausted. According to NICE guidance, non-surgical options such as activity modification, structured physiotherapy, and pain management are explored first. Surgery is then considered when symptoms persist and imaging confirms nerve compression that correlates with these symptoms.
Who is it for?
Lumbar decompression surgery is suitable for adults experiencing leg symptoms caused by identifiable pressure on the lumbar nerves. Typical symptoms include:
- Pain, aching, or cramping in the buttocks, thighs, or calves that occurs with walking or standing and eases when sitting or leaning forward, often referred to as neurogenic claudication.
- Sciatica-type pain radiating down one or both legs.
- Pins and needles, numbness, or a heavy feeling in the legs.
- Weakness affecting the foot or ankle, such as difficulty lifting the foot.
- A steadily reducing walking distance that limits work, shopping, exercise, or social activities.
- Symptoms that have not improved despite several months of appropriate conservative treatment.
Research indicates that lumbar decompression surgery tends to alleviate leg symptoms more effectively than back pain alone. Patients whose main issue is chronic lower back pain without nerve compression may benefit more from alternative approaches.
How treatment works
Assessment
A full history and examination, with an MRI usually the key investigation to confirm the level and cause of nerve compression.
Discussion of options
Continued conservative care, decompression alone, or decompression with fusion are set out, with the benefits and risks of each.
Decompression
Bone and thickened ligament are carefully removed under magnification to free the compressed nerve, often through a small incision.
Recovery
Walking is encouraged the same day, with a graded return to activity and physiotherapy over the following weeks.
Risks and Honest Expectations
Lumbar decompression is a well-established procedure, but like all surgery it carries risk. These may include infection of the wound or, rarely, deeper tissues; bleeding or a collection of blood requiring further treatment; a small tear in the lining around the nerves with spinal fluid leakage; nerve irritation or injury causing new or persisting pain, numbness or weakness; blood clots in the leg or lung; anaesthetic complications; incomplete relief of symptoms or recurrence of narrowing or disc prolapse over time; and the possible need for further surgery, including fusion, in a minority of cases.
Leg pain relief is generally more predictable than back pain relief; back pain may improve somewhat but less reliably. Recovery of nerve function can be slow and is not always complete, particularly where numbness or weakness has been present for a long time. Smoking, poorly controlled diabetes, obesity and certain medications can affect healing, so optimising general health beforehand may improve the overall experience.
Surgery is only recommended when non-surgical care has been fully explored and when it is genuinely the right option for the patient.
QUICK FACTS
Procedure time
1 to 2 hours, single level
Anaesthetic
General, or spinal in some cases
Hospital stay
Day case to 3 nights
Walking
Within a day of surgery
Back to desk work
A few weeks
Continued improvement
3 to 6 months