
Overview
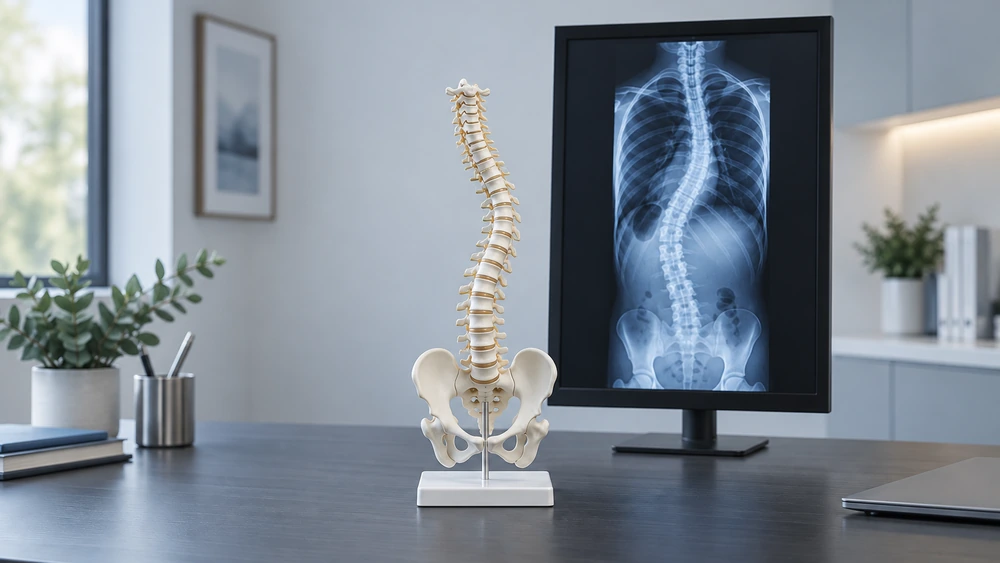
Scoliosis is a sideways curvature of the spine, often with an element of rotation. It can develop in childhood, during the adolescent growth spurt, or later in life through degenerative change. Research indicates that about 2-3% of the population is affected by scoliosis, and many curves are mild and never require surgical intervention.
When the curve is significant, progressive, or causing pain or nerve pressure, scoliosis surgery may be discussed. The most common approach in the UK is posterior spinal fusion, which uses screws and rods to hold the corrected spine in place while the treated segments fuse over several months.
Who it's for
Scoliosis surgery may be considered for individuals with:
- A significant curve that has continued to increase on repeated X-rays.
- Adolescent idiopathic scoliosis with a curve beyond the bracing effectiveness.
- Persistent back pain linked to scoliosis that has not responded to non-surgical treatments.
- Visible trunk asymmetry causing distress or functional difficulty.
- Adult degenerative scoliosis with nerve compression symptoms.
- Scoliosis linked to a neuromuscular condition affecting breathing or mobility.
- Reduced exercise tolerance or breathing difficulty in large thoracic curves.
How treatment works
Assessment
A full history and examination, with standing full-length X-rays to measure the curve and its flexibility. MRI or CT is used in selected cases.
Discussion of options
Monitoring, physiotherapy, bracing and surgery are set out, with the reasoning behind each and the consequences of doing nothing.
Correction
Where surgery is right, it is carried out under general anaesthetic with spinal cord monitoring throughout, using posterior fusion to correct and stabilise the curve.
Recovery
Structured rehabilitation follows, with interval X-rays to check alignment and healing as the spine fuses over several months.
Risks and Honest Expectations
Most people with scoliosis never need surgery. When an operation is appropriate, risks include bleeding, infection, blood clots, wound healing problems, implant issues, incomplete fusion, and the general risks associated with anaesthesia. Rarely, nerve / spinal cord injury or further surgery may be required.
The aim is to create a balanced, stable spine rather than a perfectly straight one. Movement is reduced in the fused section, although most patients adapt well. Recovery and long-term outcomes vary between individuals.
Limitations worth understanding:
- Surgery aims to improve alignment, not to create a perfectly straight spine
- Some spinal flexibility is lost at the fused levels
- Pain relief cannot be guaranteed, particularly where pain has several causes
Surgery is only recommended when non-surgical care has been fully explored and it is genuinely the right option.
Early Detection & Timely Diagnosis
Progressive spinal curvature can develop rapidly during growth spurts, making early recognition critical for effective management of progressive spinal deformity in children and adolescents. Mr Sudarshan Munigangaiah led the national ABCD early-detection initiative in collaboration with Scoliosis Support and Research (SSR), establishing a simple, memorable checklist for parents, educators, and GPs to identify early signs of scoliosis and secure timely specialist assessment before severe curves require major corrective intervention.

QUICK FACTS
Suitable for
Children and adults
Procedure time
Several hours
Anaesthetic
General
Hospital stay
Several days
Back to desk work
A few weeks
Full recovery
Several months